
Typography and Interface Choices in 3D Medical Visualization
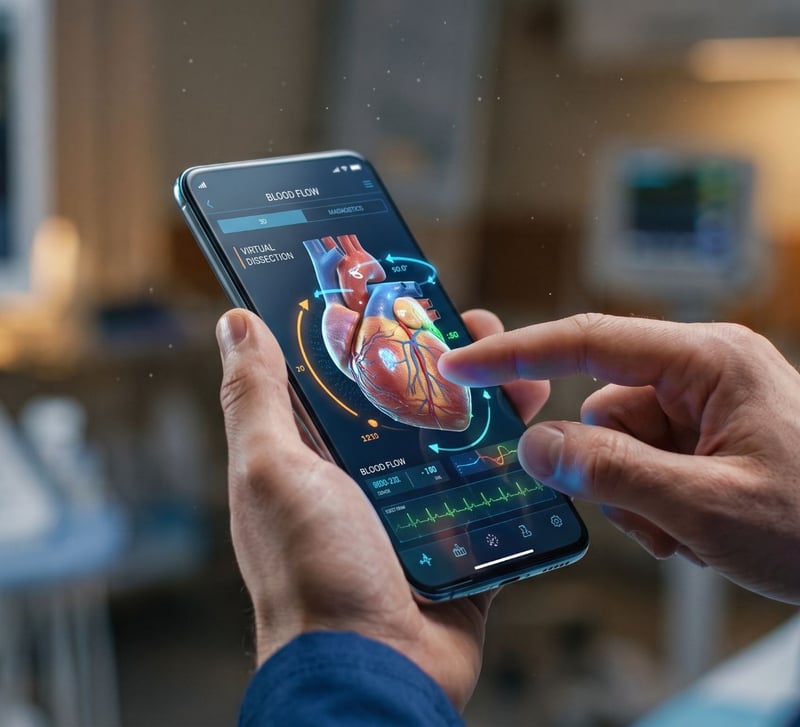
A 3D heart model can show more than any textbook figure and overwhelm the viewer in seconds. Dozens of structures sit close together, the model rotates, and every label competes with textures, shadows, and color-coded pathology.
In dense anatomy and pathology interfaces, typography and layout determine whether users find the right structure or misread it. Studios that build 3D anatomy and pathology content, such as VOKA, work at this intersection every day.
However, a model can be anatomically correct and still inefficient if people can’t read it. Therefore, companies should focus on many vital traits that ensure comprehension in medical visualization.
Why medical interfaces need their own typography rules
Medical interfaces carry a higher cost of error than most software. A student who confuses the ileum with the ilium learns the wrong anatomy. A patient who misreads a pathology highlight may misunderstand their own diagnosis.
Three conditions make 3D medical visualization harder than flat healthcare UI design:
- The background never stays still. As the model rotates, a label may sit over pale bone one moment and dark muscle the next.
- Terminology is long and precise. Latin terms such as musculus sternocleidomastoideus exceed 30 characters, and a couple of missed letters can point to a different structure.
- Audiences differ widely. The same model may serve a surgeon, a first-year student, and a patient in a waiting room.
Build visual hierarchy before choosing fonts
Visual hierarchy tells the eye what to find first. In a dense anatomy view, that order should follow the learning or clinical goal, not the order in which structures were modeled.
A practical hierarchy for medical UI design has three levels:
- Focus structure. The organ, lesion, or vessel the screen is about. It gets the largest type, the strongest weight, and the highest contrast.
- Context structures. Neighboring anatomy that helps with orientation. These labels use a smaller size and a lighter weight.
- Supporting information. Measurements, view names, and controls. This layer stays quiet until the user needs it.
Limit the interface to three or four type sizes and two weights. Each extra style adds one more decision for the reader. Apply the same logic to the 3D scene: dim or desaturate surrounding tissue when a pathology is highlighted, so the label and the structure point to the same place.
Hierarchy also depends on what stays hidden. Showing every label at once flattens the hierarchy, because nothing stands out. Progressive disclosure, where secondary labels appear on hover, tap, or zoom, keeps the focus structure clear.
Label placement for anatomy labels in 3D space
Label placement has a measurable effect on learning. Research on the spatial contiguity principle shows that people learn better when text sits close to the image it describes. A 2006 meta-analysis of 50 studies by Paul Ginns found a large effect for integrating words and graphics. In 3D anatomy, this means a label should stay near its structure, not in a legend at the edge of the screen.
Rotation makes this harder. Good anatomy labels in an interactive scene follow a few rules:
- Anchor each label to a point on the structure, and connect it with a thin leader line when space is tight.
- Keep text facing the viewer as the model turns, so it never appears mirrored or skewed.
- Prevent collisions. When labels overlap, move or hide the less important ones first, following the hierarchy.
- Fade labels for structures that rotate out of view, so users do not link a label to the wrong tissue.
- Never cover the labeled structure. Place text over space or a neutral area of the scene.
Leader lines need the same care as text. A line that crosses three structures before reaching its target forces the user to trace it, which brings back the split attention the label was meant to prevent.
Color contrast accessibility on shifting 3D backgrounds
Color contrast accessibility is harder in 3D than on a flat page, because the background changes with every rotation. Text that passes a contrast check over pale bone may fail over red muscle a second later.
The WCAG 2.2 contrast guidelines set a minimum ratio of 4.5:1 for normal text and 3:1 for large text. The non-text contrast criterion asks for 3:1 for interface components and meaningful graphics, such as leader lines and highlight outlines. In a moving scene, designers usually meet these numbers with one of three techniques:
- A semi-opaque panel behind each label;
- A thin outline or halo around the letters;
- A background tint that adapts to the tissue behind the label.
Color coding needs the same care. Pathology views often use red for inflammation or ischemia and green for healthy tissue. Pair every color with a second cue, such as a pattern, an outline, an icon, or a text label, so the meaning survives without hue.
Type choices that stay readable at small sizes
Typeface selection in medical UI design mostly comes down to legibility under real conditions. Labels are often small and read on a tablet in a clinic or a phone during a study session.
A sans-serif typeface works well when it offers:
- Clear differences between similar characters, such as I, l, and 1, or O and 0;
- A tall x-height, which keeps long terms readable at small sizes;
- Tabular figures, so measurements line up in panels and tables;
- Full support for diacritics and non-Latin scripts if the product is localized.
Avoid all caps for anatomy labels. Long capitalized terms take up more space and are harder to scan.
Plan for text expansion as well. A label that fits in English may break the layout in German or another language with longer terms. Test every label in the longest supported language before release.
A quick pre-release test for medical UI design
A short test catches most typography problems before users do. The steps are the following:
- Rotate the model a full 360 degrees and check that every label stays readable.
- View the interface on the smallest screen you support.
- Run the color palette through a color vision deficiency simulator.
- Load the longest language version and look for clipped or overlapping labels.
- Ask a clinician to confirm that each label points to the correct structure.
Clarity is part of accuracy
In medical visualization, a detailed model helps only when people can read it. Visual hierarchy guides attention, careful label placement keeps words next to structures, strong contrast makes labels readable for everyone, and well-chosen type holds up on small screens. Treat these choices with the same rigor as anatomical accuracy, because for the user they are part of the same result.